
What Does Arthritis Look Like on an X-Ray? Signs Explained
Arthritis may appear on an X-ray as:
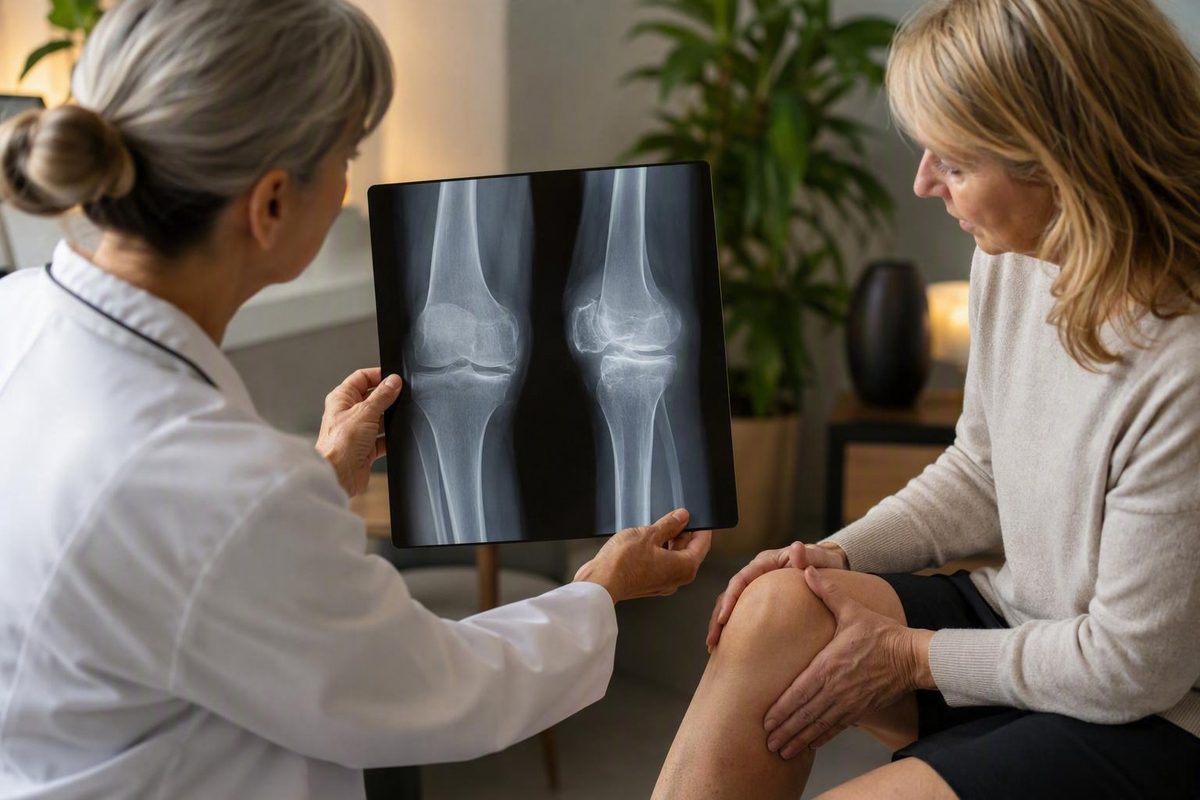
The short answer: what arthritis usually looks like on an X-ray
Arthritis may appear on an X-ray as:
- A smaller gap between bones, called joint-space narrowing
- Bony projections at joint margins, called osteophytes or bone spurs
- Brighter, denser bone beneath the joint surface, called subchondral sclerosis
- Small darker areas within nearby bone, often described as subchondral cysts
- Localized areas of bone loss, called erosions
- Altered alignment, partial displacement, remodeling, or deformity
These are common radiographic signs, but they do not all appear in every person or every type of arthritis. Osteoarthritis, rheumatoid arthritis, psoriatic arthritis, gout, and other joint diseases can produce different combinations and distributions of abnormalities. No single sign establishes the diagnosis by itself, and some findings overlap among conditions, as outlined in this radiology overview of arthritis patterns.
The crucial distinction is between what an X-ray shows directly and what clinicians infer from it. Radiographs show bones, their alignment, and the apparent space between them. Routine articular cartilage is not directly visible.
When the gap between two bones becomes smaller, clinicians may infer that the cartilage occupying that part of the joint has thinned. The image therefore shows reduced joint space, not the missing cartilage itself. Positioning, projection, joint anatomy, and the amount of load passing through the joint can all affect the apparent width.
A relatively normal joint generally has:
- Reasonably even joint spacing
- Smooth bone margins
- Fairly uniform density beneath the joint surface
- Normal alignment between the participating bones
An arthritic joint may instead have uneven or uniform narrowing, irregular or enlarged margins, altered bone density, erosions, or changes in alignment. The exact combination depends on the affected joint, arthritis type, disease stage, and imaging technique.
These descriptions are general rather than diagnostic. A qualified clinician or radiologist must interpret a personal X-ray in the context of age, symptoms, examination findings, medical history, and the complete image series.
A visual glossary of the most common X-ray findings
Radiology reports compress complicated appearances into a few technical terms. The following glossary explains what those terms usually mean without turning them into do-it-yourself diagnoses.
| Report term | Plain-language meaning | What it may look like | Patterns in which it may occur |
|---|---|---|---|
| Joint-space narrowing | The visible gap between adjacent bones is reduced | Bones appear closer together in part or all of the joint | Osteoarthritis and inflammatory arthritis, although the distribution may differ |
| Osteophyte | Extra bone at a joint margin; also called a bone spur | A point, lip, ridge, or projection extending from the bone edge | Especially common in osteoarthritis |
| Subchondral sclerosis | Increased density in the bone immediately beneath the joint surface | A brighter or whiter band near the joint | Common in osteoarthritis |
| Subchondral cyst | A small cyst-like area in bone close to the joint surface | A relatively dark, rounded or irregular area within bone | May accompany osteoarthritis and other joint disorders |
| Erosion | A localized area where bone has been lost | A notch, defect, or “bite” at or near the joint margin | Often associated with inflammatory or crystal arthritis, but not diagnostic by itself |
| Malalignment | The bones no longer line up along the expected axis | The joint tilts, angles, or bears load unevenly | Advanced degenerative or inflammatory disease; previous injury may also contribute |
| Subluxation | The joint surfaces have partially shifted out of their usual relationship | One bone is partly displaced relative to another | May occur in advanced inflammatory or degenerative arthritis |
| Deformity or remodeling | The shape of the joint or adjacent bone has changed | Flattening, enlargement, angulation, collapse, or an altered contour | More established structural disease |
This combination of narrowing, osteophytes, sclerosis, cysts, erosions, and alignment changes is supported by clinical imaging descriptions of arthritis, including the Hospital for Special Surgery overview of osteoarthritis imaging.
Joint-space narrowing is an indirect marker of cartilage loss. Because cartilage is not visible on a routine radiograph, clinicians assess the space that it normally helps maintain between bones. Narrowing may be focal, uneven, uniform, or limited to one compartment of a joint.
An osteophyte is attached extra bone at a joint margin. It may look like a sharp point or a broad ridge.
Subchondral sclerosis means that bone immediately beneath the joint surface has become denser. Denser bone absorbs more X-rays and therefore appears relatively brighter or whiter.
A subchondral cyst appears as a relatively darker area in bone near the affected surface. It does not mean that every dark area beside a joint is an arthritis cyst; location, margins, accompanying changes, and the complete image series matter.
An erosion is a focal defect caused by bone loss. Marginal erosions near the edge of a joint may support suspicion of inflammatory arthritis, while other erosion patterns can occur in gout, psoriatic arthritis, and erosive osteoarthritis. An erosion is therefore a clue rather than an independent diagnosis.
Malalignment means that the bones meet at an altered angle. Deformity is a broader term for a lasting change in joint shape or the relationship between adjacent bones.
Other findings may include soft-tissue swelling, reduced bone density around a joint, fluid, loose bodies, or calcium deposits. These are not universal signs of arthritis. Calcium deposition in a characteristic distribution, for example, may suggest calcium pyrophosphate deposition disease rather than routine osteoarthritis.
From mild narrowing to advanced bone-on-bone change
Arthritis does not always advance through a neat sequence. Different parts of the same joint can change at different rates, and an X-ray captures structure only at a particular time and in a particular position. Radiologists nevertheless use terms such as mild, moderate, and severe to summarize the visible extent of disease.
Mild osteoarthritis may show:
- Slight or uneven joint-space narrowing
- Small osteophytes at one or more margins
- Minimal change in the bone beneath the joint
- Little or no visible alteration in alignment
Reports may use phrases such as “minimal degenerative change,” “early osteoarthrosis,” or “mild compartmental narrowing.” Positioning can affect how conspicuous these subtle changes appear.
Moderate osteoarthritis may show:
- Clearer or more extensive narrowing
- More visible osteophytes
- Increased subchondral density
- Possible cyst-like changes
- Early remodeling of the joint surfaces
- Some change in alignment
Advanced osteoarthritis may show:
- Severe or nearly complete loss of the visible joint space
- Apparent contact between opposing bone surfaces
- Larger osteophytes
- Substantial sclerosis
- More extensive cyst-like change
- Flattening, remodeling, angulation, or deformity
- Subluxation or marked malalignment
“Bone-on-bone” is an informal description of little or no visible gap between opposing bone surfaces on the relevant view. Osteoarthritis can be present long before this appearance develops.
For knee osteoarthritis, one commonly used classification is the Kellgren–Lawrence scale:
- Grade 0: No radiographic evidence of osteoarthritis
- Grade 1: Doubtful change
- Grade 2: Mild osteoarthritis
- Grade 3: Moderate osteoarthritis
- Grade 4: Severe osteoarthritis
Because grade 0 is included, this is a five-level scale. The grade definitions and their limitations are explained in this physician-authored guide to knee arthritis X-ray grades.
Structural grade and lived experience are not interchangeable. A person with advanced-looking changes may remain active with manageable symptoms, while someone with less extensive findings may have substantial pain, stiffness, or limitation. X-ray severity answers a narrow question—how much structural change is visible—but cannot independently measure pain or determine which finding is responsible for it.
Osteoarthritis versus inflammatory arthritis on X-ray
An X-ray can provide clues that favor a degenerative or inflammatory pattern, but it cannot establish the exact arthritis subtype by itself. Interpretation depends on the combination of findings, the joints involved, symmetry, age, symptoms, physical examination, and sometimes laboratory or joint-fluid tests.
The broad contrast is:
- Typical osteoarthritis: often uneven or asymmetric joint-space loss accompanied by bone proliferation, especially osteophytes and subchondral sclerosis
- Inflammatory arthritis: may show more uniform or symmetric loss of joint space, marginal erosions, reduced bone density near the joint, swelling, subluxation, or deformity
These are tendencies rather than rules. Early inflammatory arthritis may have no visible erosions, while established osteoarthritis can become markedly deformed. Trauma, infection, crystal deposition, and other joint disorders can also create atypical appearances.
| Condition | Common X-ray pattern | Distribution clues | Important limitation |
|---|---|---|---|
| Osteoarthritis | Uneven narrowing, osteophytes, subchondral sclerosis, possible cysts and later deformity | Often compartment-specific; in the hand, frequently affects DIP joints and the thumb-base CMC joint | Similar degeneration can occur after injury or alongside another condition |
| Rheumatoid arthritis | More uniform narrowing, marginal erosions, periarticular loss of bone density, and later subluxation or deformity | Often symmetric; commonly involves wrists, MCP joints, and PIP joints while generally sparing DIP joints | Early films may be normal, and no single erosion proves rheumatoid arthritis |
| Psoriatic arthritis | Erosions combined with new bone formation; sometimes a pencil-in-cup appearance | May involve DIP joints and may be asymmetric | A distinctive pattern is a clue, not proof |
| Gout | Eccentric or punched-out erosions, sometimes with overhanging edges | May concentrate around particular joints, including the first MTP joint | Joint space may remain relatively preserved until later; confirmation may require fluid analysis |
| Erosive osteoarthritis | Central erosions combined with osteophytes, potentially creating a gull-wing contour | Often affects interphalangeal joints of the hands | It can overlap visually with inflammatory disease |
| CPPD | Chondrocalcinosis in characteristic locations, sometimes with an atypical degenerative pattern | Distribution may differ from primary osteoarthritis | Calcification alone does not settle the diagnosis |
These comparisons reflect recognized radiographic tendencies, but there is substantial overlap among joint diseases. Distribution and associated bone changes are central to interpretation, as shown in a systematic radiology approach to arthritis X-rays.
In the hands, osteoarthritis often affects the distal interphalangeal joints, or DIPs, nearest the fingertips, and the carpometacarpal joint, or CMC, at the base of the thumb. Those joints may show narrowing, spurs, cyst-like changes, enlargement, or crooked remodeling.
Rheumatoid arthritis more commonly affects the wrists, metacarpophalangeal joints at the knuckles, and proximal interphalangeal joints in the middle of the fingers. It generally spares the DIPs. Rheumatoid changes may include uniform narrowing, marginal erosions, reduced bone density near the joint, and—later—subluxation or deformity.
Several memorable report terms describe particular patterns:
- Pencil-in-cup: erosion and remodeling that may occur in psoriatic arthritis
- Punched-out erosion with an overhanging edge: a pattern that may suggest gout
- Gull-wing appearance: central erosions combined with osteophytes in erosive osteoarthritis
- Chondrocalcinosis: cartilage calcification that may suggest CPPD in the appropriate location and clinical setting
None should be treated as a home diagnostic test. Real cases may be incomplete, atypical, or affected by more than one process.
How arthritis appearances vary in the knee, hand, hip, and spine
The core signs overlap across the body, but their location and distribution vary by joint. Projection, positioning, weight-bearing status, and the anatomy being imaged can all change how severe a finding appears.
Knee
The knee contains several articular regions rather than one uniform space. Osteoarthritis may affect:
- The medial compartment on the inner side
- The lateral compartment on the outer side
- The patellofemoral compartment between the kneecap and thigh bone
- Two or all three compartments
This describes distribution, not symptom intensity.
The medial compartment is commonly affected, although any compartment may be the main site of disease. Predominant inner-compartment loss can contribute to varus, or bowlegged, alignment. Predominant outer-compartment loss can contribute to valgus, or knock-kneed, alignment.
Standing, weight-bearing knee radiographs may make compartmental narrowing more apparent because loading places the joint surfaces in their functional relationship. Non-weight-bearing images are not automatically inadequate; they evaluate the joint under different mechanical conditions.
A knee series may include a standing front-to-back view, a lateral view, and one or more kneecap views. A bent-knee standing view may also be obtained. There is no single protocol for every patient, but these commonly described views and the role of loading are summarized in the knee arthritis imaging guide.
Hand
Hand osteoarthritis frequently involves the DIP joints nearest the fingertips and the thumb-base CMC joint. Findings may include localized or uneven narrowing, osteophytes, sclerosis, cyst-like areas, enlargement, and crooked remodeling.
Because many small joints appear on one hand radiograph, distribution can be as informative as the appearance of an individual joint. A pattern concentrated at the DIPs and thumb base suggests something different from a symmetric pattern centered on the wrists, knuckles, and PIPs. Examples of the common hand distribution are described by this specialist hand-clinic overview.
Hip
Hip osteoarthritis may show focal or more extensive narrowing, osteophytes around the femoral head or socket, subchondral sclerosis, cyst-like changes, and remodeling.
Advanced remodeling can alter the contour of the femoral head or socket. Even then, an abnormal-looking hip does not prove that every symptom in the groin, thigh, buttock, or back arises from that finding.
Spine
Spinal degeneration is not identical to arthritis in a knee, hip, or finger. The spine includes intervertebral discs, facet joints, vertebral bodies, ligaments, and multiple alignment relationships. Radiographic findings may include reduced spacing between vertebrae or loss of disc height, vertebral osteophytes, facet-joint changes, slippage, curvature, or altered alignment.
The disc itself is not displayed like bone; disc-height loss is inferred from reduced spacing between adjacent vertebral bodies.
Across all joints, comparison is most meaningful when images use similar views, positioning, and loading. A difference between two films may represent progression, but technique can also make spacing or alignment look different.
Can you have arthritis with a normal X-ray?
Yes. A normal X-ray does not rule out early osteoarthritis or inflammatory arthritis.
Routine radiographs are strongest at showing established changes in bone, spacing, alignment, and joint shape. They are less capable of depicting early synovial inflammation, subtle cartilage injury, ligaments, tendons, and many other soft-tissue abnormalities. Inflammatory pain, swelling, and stiffness may begin before erosions or uniform narrowing become visible. Osteoarthritis symptoms can also occur before standard radiographs show definite degeneration.
This is why imaging must be matched to the clinical question:
- MRI can show cartilage, bone-marrow edema, inflammation, ligaments, the joint lining, and other soft tissues that routine X-rays may miss.
- Ultrasound may show joint fluid, synovitis, increased blood flow associated with active inflammation, tendon abnormalities, and some small erosions.
- CT provides highly detailed bone images and may help assess deep or anatomically complex regions, particularly in parts of the spine or pelvis.
The choice among these methods depends on the joint, symptoms, examination, suspected condition, and the specific unanswered question, according to the RadiologyInfo patient guide to arthritis imaging.
A normal film means only that the radiograph did not show definite abnormalities under the conditions of that examination. It does not mean that symptoms are imaginary, that no joint disorder exists, or that advanced imaging is automatically necessary.
Whether another test would be useful depends on:
- The symptom pattern
- The joint or tissues thought to be involved
- Examination findings
- The suspected condition
- Whether signs of inflammation are present
- Whether the answer would change clinical management
Why the X-ray may not match your pain
A worse-looking X-ray does not reliably mean worse pain, stiffness, or disability.
An X-ray describes visible structure. Pain and function are clinical experiences that are not fully represented by joint-space width, osteophyte size, or an assigned image grade. Some people have substantial structural changes but manageable symptoms. Others report marked pain and limitation despite relatively mild abnormalities or a normal radiograph.
This mismatch is not a reason to dismiss either the image or the symptoms. It means they must be interpreted together. A radiologist may accurately describe severe degeneration while the person reports modest limitations. Conversely, a painful joint with little radiographic osteoarthritis may require assessment for early disease or another source of symptoms.
Degenerative findings can also exist without being the primary cause of the current complaint. A spur discovered during a pain investigation does not automatically prove that the spur is generating the pain. Mild narrowing may be relevant, incidental, or only one part of the clinical picture. The limited correlation between radiographic severity and symptoms is also emphasized in this clinical comparison of osteoarthritis and rheumatoid arthritis.
Clinicians try to connect imaging with:
- The precise location of pain
- Whether symptoms are constant or activity-related
- The onset and duration
- Morning or rest-related stiffness
- Swelling, warmth, or reduced movement
- Tenderness and mechanical findings on examination
- Previous injury or surgery
- Effects on walking, stairs, gripping, work, sleep, and other activities
A more useful question than “Does this X-ray show arthritis?” is: “Do the location and pattern of these changes plausibly match this person’s symptoms?” The answer may be yes, partly, or no.
How an arthritis X-ray is interpreted—and what to do with the result
An arthritis X-ray is one component of an evaluation, not a standalone diagnosis. The radiology report describes what is visible; the clinician determines how those observations fit the person’s health and symptoms.
Relevant information includes:
- When symptoms began and how they have changed
- Which joints are affected
- Whether the pattern is symmetric
- Whether symptoms are localized or widespread
- The duration and pattern of stiffness
- Swelling, warmth, tenderness, and range of motion
- Previous injuries, surgery, infections, or medical conditions
- Family and medication history where relevant
- Functional effects, such as difficulty walking, gripping, climbing stairs, or working
If inflammatory arthritis is suspected, blood tests may be used to look for inflammation or supportive immune markers. No single blood test establishes every inflammatory diagnosis. Physical examination, laboratory testing, fluid analysis, and different imaging methods may all contribute to an arthritis evaluation, rather than an X-ray acting as conclusive proof (RadiologyInfo).
Serial X-rays can establish a structural baseline and show change over time. Comparisons are more meaningful when the same joint is imaged using similar projections, positioning, and weight-bearing conditions. If the techniques differ, part of an apparent change may result from image acquisition.
Questions worth asking about a report include:
- Was the image taken while I was bearing weight?
- Which joint or compartment is affected?
- Is the narrowing focal, uniform, or asymmetric?
- What does each technical term mean?
- Are erosions, osteophytes, sclerosis, cysts, or malalignment present?
- Does the finding match the location of my symptoms?
- Is the appearance typical of osteoarthritis, suggestive of inflammation, or nonspecific?
- Would another view or imaging method answer an unresolved question?
- If earlier images exist, were they obtained in a comparable way?
A hot or markedly swollen single joint warrants clinical assessment because an X-ray cannot distinguish all possible causes. Infection, crystal arthritis, injury, and other disorders can overlap in presentation.
A clinician or radiologist with access to the full images, report, history, and examination is the appropriate person to interpret personal results.
The central takeaway is that a classic arthritic X-ray combines changes in joint spacing, bone margins, bone density, and alignment. The pattern depends on the joint, condition, stage, and imaging technique. Cartilage loss is inferred rather than directly seen, early arthritis can be invisible, and structural severity may not match symptoms. A report is most useful when interpreted alongside the person’s history, examination, and—when appropriate—laboratory tests or additional imaging.
Frequently asked questions
What is the first sign of arthritis on an X-ray?
There is no universal first sign. In osteoarthritis, subtle uneven joint-space narrowing or a small osteophyte may be among the earliest visible changes. In inflammatory arthritis, radiographs may remain normal even after pain, swelling, and stiffness have begun.
Joint-space narrowing can suggest cartilage loss, but it must be judged against positioning, anatomy, and the rest of the image. A single narrow-looking space does not automatically prove arthritis, as explained in this clinical review of X-ray signs and early disease limitations.
What does bone-on-bone arthritis look like?
“Bone-on-bone” describes little or no visible joint gap between opposing bone surfaces on the relevant X-ray view. Associated advanced findings may include larger osteophytes, pronounced sclerosis, cyst-like areas, remodeling, and altered alignment.
The phrase is informal rather than a complete diagnosis. It does not necessarily mean that every part of the joint lacks cartilage, and this appearance is not required for arthritis to be present (Hospital for Special Surgery).
Can an X-ray show cartilage damage?
Not directly on a routine radiograph. X-rays show bones and the apparent space between them, so clinicians infer cartilage loss when that space becomes narrower.
MRI can display cartilage and other soft tissues in greater detail. Whether MRI would be useful depends on the symptoms, examination, suspected diagnosis, and the specific question left unanswered by the X-ray, as described in this arthritis imaging overview.
Can arthritis be present even when an X-ray is normal?
Yes. Early osteoarthritis and early inflammatory arthritis may not produce visible abnormalities on routine radiographs. X-rays are better at showing established bone and structural changes than early synovial inflammation, subtle cartilage injury, or many soft-tissue abnormalities.
A normal film therefore does not rule out arthritis. It also does not mean everyone needs advanced imaging; next steps depend on the clinical evaluation and the question another test would answer (GoodRx).
Why are knee X-rays sometimes taken while standing?
Standing places weight through the knee and may make compartmental joint-space narrowing more apparent. An unloaded image can show a wider gap because the joint surfaces are not being assessed under the same mechanical conditions.
Weight-bearing status is only one part of technique. Beam direction, knee position, degree of bending, and the selected views can also alter apparent spacing and alignment. Comparisons are therefore most reliable when images are obtained in similar ways.